Why Do Some People Respond Better to GLP-1s?
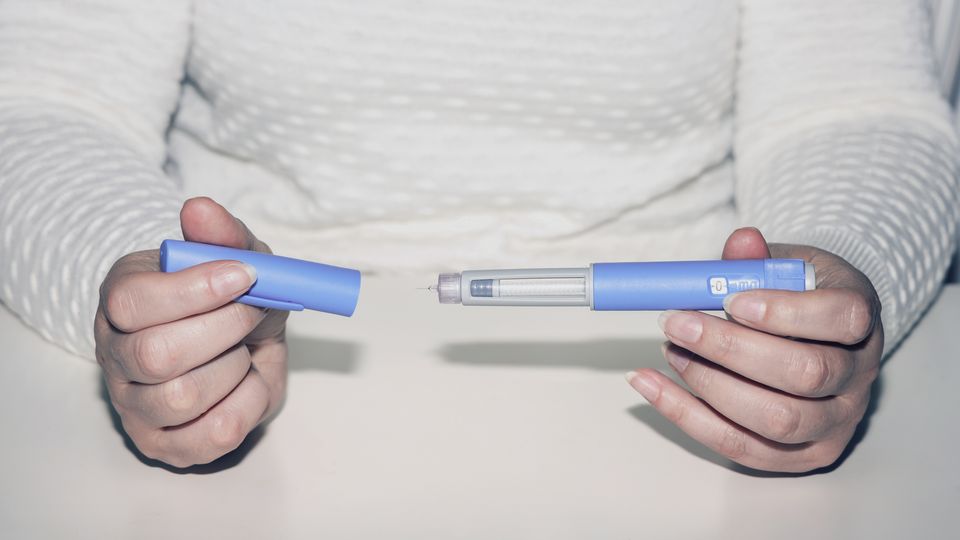
Individuals with rapid gastric emptying and low GLP-1 levels lost more body weight with tirzepatide.
Why does weight seem to come off easily for some people, while others struggle despite doing everything “right?”
Mayo Clinic researchers may have just revealed part of the answer.
In new research, published in Gastroenterology, three subtypes of obesity were identified. The subtypes may explain variable responses to glucagon-like peptide-1 (GLP-1) therapy. In one subtype, individuals had lower GLP-1 hormone levels; this group responded best to the dual GLP-1/glucose-dependent insulinotropic polypeptide (GIP) agonist tirzepatide, losing 21.5% body weight in six months.
Obesity is more complex than “calories in, calories out”
GLP-1 receptor agonists were first developed to treat diabetes. The approval of GLP-1s for obesity management came later, after clinicians observed that some patients benefited from significant reductions in body weight with the treatment, although the response varied between individuals.
About GLP-1
GLP-1 is a naturally occurring hormone. It is released by cells in the intestine after a meal. The hormone acts on the GLP-1 receptor to induce several effects: it slows gastric emptying, increases satiety, and acts on the endocrine system to help control blood glucose.
The phrase “calories in, calories out” will be familiar to health-conscious folk and fitness fanatics alike. In essence, burn more calories than you consume, and weight loss will follow.
But scientists are increasingly recognizing that weight regulation is more complicated than this simple formula might suggest.
For example, food intake is only half of the equation. This half alone is governed by three primary processes—hunger, satiation (or fullness), and the time in between the two—each with its own intricacies.
Different obesity subtypes have been linked to dysfunction across such processes.
“In this study, we took that a step further,” noted lead author of the new study, Dr. Andres Acosta, gastroenterologist and Delaney Family Director of the Nutrition Obesity Research Program at Mayo Clinic.
The researchers aimed to understand why certain individuals feel hungry between meals, and how their gastrointestinal hormones might contribute.
Understanding different obesity subtypes
Adults aged 18–65 years were enrolled in the study (N=483). Exclusion criteria included a history of weight loss medication use in the last six months, pregnancy, uncontrolled systemic disease, and conditions/past surgeries that may interfere with gastric motility and absorption.
Participants ate radiolabeled, standardized breakfast meals. Single-photon emission computerized tomography was performed at baseline and then at regular intervals thereafter to calculate gastric emptying time. Blood samples were also collected at baseline and at regular intervals to assess enteroendocrine hormone levels.
Around lunchtime, four hours after the standardized breakfast, participants were given an ad libitum meal; they had unrestricted access to food and could eat as much as they wanted.
Subjective feelings of hunger and psychological traits related to intake, such as emotional eating, were assessed using the Visual Analogue Scale and the Three-Factor Eating Questionnaire, respectively.
Stool samples were collected for fecal microbial analysis, and intestinal biopsies from 31 participants were analyzed to assess GCG and PYY mRNA expression.
GCG and PYY
GCG encodes a proglucagon-derived peptide hormone precursor to GLP-1 and other hormones. PYY encodes the precursor to peptide YY (PYY). PYY plays a role in appetite regulation, and is released by intestinal cells in a nutrient-dependent manner.


Inflammatory Protein Biomarkers in Clinical Studies
Explore how inflammatory protein profiling revealed treatment effects and distinct Long COVID/ME-CFS signatures, and discover how these approaches can support biomarker discovery, patient stratification and longitudinal research.View Webinar
“We found three groups that explain the pathophysiology of obesity in patients. The first group has normal hunger between meals, normal gastric emptying, and normal GLP-1 levels.”
“The second group feels hungry in between meals, they have rapid gastric emptying, and they have very high levels of GLP-1, which is interesting and pathological in itself. Why would you have rapid gastric emptying and feel hungry between meals when you have high GLP-1?”
“The third group feels hungry and has rapid gastric emptying between meals, as in group two, but they have very low GLP-1 levels.”
“There's clearly a disconnect between your hunger sensation and your GLP-1 levels.” — Dr. Andres Acosta.
These findings may help explain why some individuals with obesity feel hungry soon after eating, which contributes to increased food intake and obesity. “It could be compared to another deficiency. A little bit like type one and type two diabetes. In type one diabetes, you don't make enough insulin, whereas in type two diabetes, you have high insulin [but are resistant].”
The team delved deeper into potential explanations. There were no significant differences in fecal microbial composition or plasma bile acids between the groups. However, several circulating short-chain fatty acids were higher in the low-GLP-1 group. Additionally, expression of mRNA from genes encoding satiety-hormone precursor genes was reduced in the cluster associated with low levels of GLP-1, rapid gastric emptying, and increased hunger between meals.
“This suggested that the problem could be within the cells that produce these hormones in our gut,” Acosta noted, highlighting this as an area for future research.
Tirzepatide “super responders” identified
A subset of the participants (n=61) had previously used tirzepatide. The researchers performed a retrospective analysis of weight loss outcomes in these individuals.


Digitalizing the Pharmaceutical GMP Laboratory Bench
Join this webinar to explore approaches to digitizing GMP laboratory workflows, from guided procedure execution and automated calculations to instrument integration and audit-ready records.View Webinar
The cluster of participants with rapid gastric emptying and low GLP-1 were classed as tirzepatide “super responders,” losing 21.5% of their body weight at six months. “That's better than bariatric surgery,” commented Acosta. Comparatively, participants in the other two clusters had an average weight loss of 11.7%.
“It makes a lot of sense because if you don't have that GLP-1, your cells aren't making it, and we've essentially replaced it with GLP-1 replacement therapy,” added Acosta.
One step closer to personalized obesity medicine
The study contributes to the growing body of evidence that obesity is much more complex than initially thought. It also lays the foundation for personalized obesity medicine.
“The reason we are conducting this research is not only to identify those with GLP-1 deficiency but also to determine who should receive treatment,” said Acosta.
The study did have limitations. For example, biopsies were taken from a small number of patients, so intestinal factors that may influence obesity require further investigation. Additionally, tirzepatide is a dual GLP-1/GIP agonist. Future studies will need to elucidate the role of GIP in the identified obesity subtypes.
“Again, I like to use the example of children who are diagnosed with diabetes. Just as insulin is used in that case, or thyroid hormone replacement is used in hypothyroidism, I see obesity medicine in a similar way.”
Reference: Ticho AL, McRae AN, Cifuentes L, et al. A Subphenotype of obesity with reduced enteroendocrine glucagon-like peptide 1 synthesis and enhanced tirzepatide response. Gastroenterology. 2026. doi: 10.1053/j.gastro.2026.05.019.
About the interviewee:
Dr. Andres Acosta is a physician, scientist, inventor, and entrepreneur. He is board-certified in internal medicine, gastroenterology and hepatology, and obesity medicine and nutrition. Dr. Acosta holds an MD from University of San Francisco de Quito and a PhD from University of Florida. Currently, he is a professor of medicine and consultant in gastroenterology and hepatology at the Mayo Clinic. He is the Delaney Family Director of the Nutrition Obesity Research Program at Mayo Clinic and the director of the Precision Medicine for Obesity Program at Mayo Clinic.
Dr. Acosta's goal is to treat and ultimately cure obesity, which he considers this century's health epidemic. He is a recognized national and international obesity and cardiometabolic disease expert with many patents and more than 155 peer-reviewed publications. His work has been featured in the New York Times, Time, CNN, and NPR, among others. Acosta co-founded Phenomix Sciences and launched the first-of-its-kind diagnostic test to predict response to GLP-1s and other obesity/metabolic interventions. This invention was featured by Time Magazine as one of the best inventions of 2024.
 Add Technology Networks as a preferred Google source to see more of our trusted coverage.