Yes, General Anesthesia Can Be Safe for C-Sections
New evidence shows that general anesthesia is a safe alternative for C-sections.
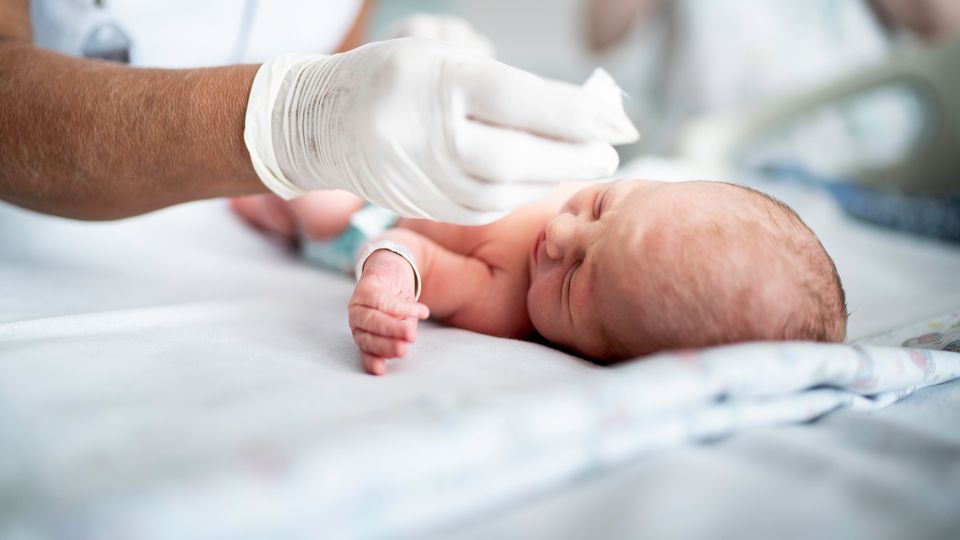
The choice of anesthesia for cesarean section (C-section) is driven by the concern that general anesthesia might harm the newborn, limiting options when a spinal or epidural fails.
A new systematic review and meta-analysis from the University of Pennsylvania now provides robust evidence that general anesthesia is a reasonable, safe alternative.
Anesthesia choice in C-section needs re-evaluation
Regional anesthesia, such as a spinal or epidural block, is often the first-line anesthetic for most C-section deliveries. Since one in three births in the United States is delivered by C-section, the choice of anesthesia carries significant clinical weight.
For decades, clinicians have worried that general anesthesia agents crossing the placenta might temporarily impact the newborn's respiratory or neurological function.
Despite this conventional standard, studies have shown that up to one in six patients receiving an epidural may still experience significant or excruciating pain during their C-section – leading to traumatic birth experiences and lasting emotional impacts.
“No patient should have to experience pain during C-section; as an anesthesiologist, I never want someone to feel forced to choose between their baby’s health and not having to experience the pain of surgery,” said corresponding author Dr. Mark Neuman, the Horatio C. Wood Professor of Anesthesiology at the University of Pennsylvania.
Clinicians are hampered by outdated evidence when advising patients on alternatives to regional anesthesia, and reliable data comparing the short- and long-term risks of general and regional anesthesia is hard to find.
To address this, Neuman and the team performed a systematic review and meta-analysis of randomized controlled trials, comparing the short-term neonatal outcomes between both anesthesia options.
Key findings from the C-section anesthesia meta-analysis
Their search identified 36 suitable trials published across 3 decades, pooling data from 3,456 neonates delivered by C-section. This large meta-analysis updates the last systematic review, which was conducted in 2005.
The analysis concentrated on three short-term measures used to assess newborn health, including Apgar scores at one and five minutes, the immediate requirement for respiratory support and the rate of Neonatal Intensive Care Unit (NICU) admission.
Apgar scores
A rapid, standardized test given to newborns at one and five minutes after birth to quickly assess their physical condition, covering heart rate, respiratory effort, muscle tone, reflex response and skin color.
Regional anesthesia was associated with a statistically significant, yet small, advantage in Apgar scores at one minute post-delivery; however, this difference largely disappeared by the five-minute mark. The risk of a low Apgar score (defined as less than seven) followed a similar pattern.
Regarding interventions, neonates under regional anesthesia were less likely to require respiratory support immediately after birth.
However, the results did not translate into worse outcomes. The study found no significant difference in the rate of NICU admission between the two anesthetic techniques.
Future C-section research needs
The results suggest that while regional anesthesia remains the primary choice, general anesthesia is a reasonable alternative for C-section delivery when medically necessary or preferred.


Ask The Expert: Navigating the Path From Discovery to Clinical Impact
Join Dr. Stella Vnook (30+ years biotech/pharma) as she explores navigating discovery to clinical impact - overcoming barriers, mitigating risk and advancing therapies to patients.View Ask The Expert
The statistically significant, yet small, differences in Apgar scores suggest the temporary impact of general anesthesia on the newborn does not translate into worse short-term outcomes.
“Since regional anesthesia is so widely used, it’s common for patients to feel that a spinal or epidural block is the only safe option for C-section. But as our study shows, anesthesia type during pregnancy does not need to be one-size-fits-all,” said Neuman.
“This study equips women with evidence-based context about the use of general anesthesia during C-section,” said lead author Dr. Sarah Langer, a resident in anesthesiology at the Perelman School of Medicine. “Childbirth is a physically and emotionally demanding process, but we do not want patients to feel like there aren’t options when it comes to their anesthesia for C-section.”
Despite pooling data from 36 trials, the authors found that all the original studies carried a high or unclear risk of bias, limiting the overall certainty of the results. When combining the Apgar score data, the individual trial results also varied widely, a statistical issue called high heterogeneity. This variation limits how much confidence can be placed in the single average result.
The paper highlights the need for new, methodologically sound trials, especially in North America, focusing on long-term neonatal health.
“For patients who are open to regional anesthesia, spinal or epidural block remains a great first-choice option. But having conversations with patients about general anesthesia doesn’t need to be taboo. Patients deserve to know they have options, and our study helps provide the evidence to support those discussions,” said Neuman.
Reference: Langer S, Lim G, Qiu Y, Biaesch J, Neuman MD. Neonatal outcomes with regional versus general anesthesia for cesarean delivery: A meta-analysis of randomized controlled trials. Anesthesiology. 2025. doi: 10.1097/ALN.0000000000005785
This article is a rework of a press release issued by the University of Pennsylvania School of Medicine. Material has been edited for length and content.
 Add Technology Networks as a preferred Google source to see more of our trusted coverage.