Could the Gut Microbiome Improve Colorectal Cancer Screening?
Researchers identified a consistent gut microbiome signature linked to colorectal cancer and early-stage disease.
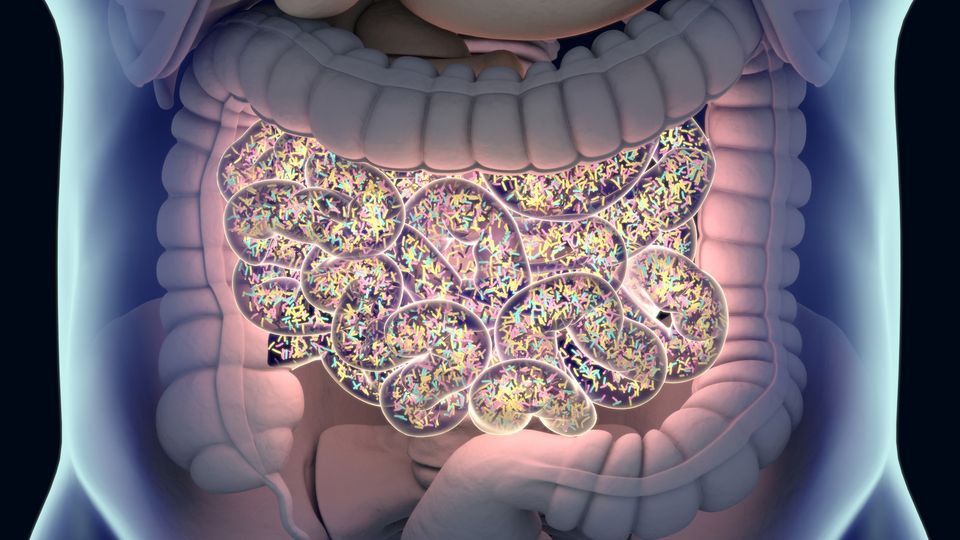
In a meta-analysis of almost 6,800 gut microbiome sequencing profiles, researchers from Leiden University Medical Center (LUMC) and the European Molecular Biology Laboratory have identified a consistent microbial signature associated with colorectal cancer (CRC).
In this interview, Prof. Georg Zeller of LUMC discusses the potential of microbiome-based cancer detection, the influence of diet on cancer-associated microbial patterns, and the challenges that must be overcome before microbiome-based diagnostics can be integrated into routine screening.
Does the presence of cancer-associated microbes in early-stage disease raise the possibility of detecting cancers before symptoms appear?
Georg Zeller, PhD (GZ):
Yes, our study indicates that that’s possible. While we don’t have systematic symptom recordings, the fact that we detected characteristic microbes in early-stage tumors and some precancerous lesions—which are usually asymptomatic—supports the notion that fecal microbiome readouts can in principle be used for early cancer detection.
Practically, the diagnostic accuracy of the models we developed based on our cross-study collection of microbiome profiles (from 25 studies that used different technologies and protocols for data generation) doesn’t quite reach the reported accuracies for diagnostic tests detecting traces of blood in stool, such as the fecal immunochemical test (FIT), or human DNA containing tumor genomic markers.
KP:
Why has it been so difficult to establish a universally accepted CRC microbiome signature until now?
GZ:
There have been several earlier studies by us and other research groups (most notably Prof. Nicola Segata’s research from the University of Trento) suggesting the existence of universal gut microbiome signatures for CRC.
Our latest study stands out in that it is based on the largest combined data set analyzed to date and shows that such a universal signature can be clearly delineated in a technically heterogeneous data set integrating both shotgun metagenomics and 16S amplicon sequencing.
We further corroborate the universality of the signature by a large-scale comparison between microbes enriched in feces of cancer patients vs at the tumor site itself, showing that they are very similar. Finally, we show that patients with early-onset cancer harbor the same characteristic microbial signature as late-onset patients.
KP:
GZ:
As we established a universal cancer classifier capturing the CRC microbiome signature that can be robustly applied to any gut microbiome dataset, we were able to re-analyze datasets for which detailed records of dietary habits were available or that come from dietary intervention studies.
We found an inverse correlation between dietary fiber (and other plant-derived dietary components) and the CRC classifier score, meaning that individuals with low fiber intake, on average, show more cancer-like microbiome patterns.
We also saw that some dietary interventions (aimed at increasing fiber consumption) could reduce the CRC microbiome score, suggesting that such interventions might be effective for cancer prevention. This is well in line with dietary risk factors for CRC established by epidemiological studies. However, the microbiome-based prevention concept critically hinges on the assumption that the relevant microbes causally contribute to carcinogenesis or cancer progression.
This is something we cannot directly address in our study, as it is observational in nature. This allows us to identify associations between microbes in the gut or mucosal tissues and CRC, but by design we cannot draw any conclusions about causation. While we found microbes present in early-stage tumors and in some tumor precursor lesions (adenomas), we can only refer to other studies that directly address mechanisms and causality. Our data cannot rule out the possibility that these microbial enrichments are a mere consequence of cancer formation (caused by other processes).
There is, however, a growing body of evidence in the scientific literature supporting a causal contribution of so-called “oncomicrobes” to cancer initiation or progression.
KP:
How close are microbiome-based approaches to becoming useful additions to current CRC screening programs?
GZ:
Current microbiome classifiers don’t quite reach the accuracies of established noninvasive diagnostic tests, even though they come close. I believe there are a few promising avenues to pursue to develop microbiome tests that meet market and patient needs.
First of all, a thorough assessment of whether fecal microbiome readouts could be combined with FIT or host-targeted tests to improve their accuracy appears very promising. This hasn’t been attempted on really large datasets (of >1000 participants from a screening population) as far as I know.
Secondly, it will be critical to develop readouts compatible with diagnostic workflows; e.g., a qPCR panel would be cheaper, reduce turnaround time, be easier to standardize, and potentially be more sensitive in detecting low-abundant microbial markers in small amounts of feces. Improved sensitivity and standardization could lead to higher diagnostic accuracies compared to what is currently possible with heterogeneous metagenomics datasets.
Finally, such a future test would have to be integrated into existing screening programs. As many European countries have population screening programs based on FIT tests, this doesn’t seem too far-fetched, but it would still require a big effort.
An exciting outlook for microbiome-based testing programs is that for several other diseases, highly predictive gut microbiome signatures have been reported, so multi-disease diagnostics with a single test might become a reality in the future.
 Add Technology Networks as a preferred Google source to see more of our trusted coverage.